Know how your chronic patients actually take their medication
DoryGo combines pre-sorted multi-dose blisters, a sensor pill box and a patient app. It records each dose as it is taken — so care teams work from real intake data, not from refill records.

Not a health system?
Same product, different entry point.
01 — The problem
Refill data tells you what was dispensed, not what was taken
Claims and pharmacy records are the standard proxy for adherence because they are the data that already exists. They answer a logistics question well and a clinical one poorly: a dispensed pack is not a taken dose, and the gap between the two is where chronic care quietly fails.
The measurement is indirect
A collected prescription says the medication left the pharmacy. It says nothing about which doses reached the patient, or when.
The signal arrives late
A missed refill becomes visible after weeks or a quarter — long after the point where a short conversation would have been enough.
Failure and non-adherence look the same
Without intake data, an unchanged HbA1c or blood pressure cannot be told apart from a therapy that was never taken as prescribed.
of plasma samples contained the study drug, while self-report and returned pill counts indicated 86–90% adherence (HIV prevention trial, women in South Africa, Uganda and Zimbabwe).
Source: Marrazzo et al., New England Journal of Medicine, 2015 (VOICE trial)
02 — The economics
Better intake shows up in your cost line, not in your drug bill
of patients in developed countries do not take medication for chronic conditions as prescribed.
saved in avoidable emergency and hospital cost per additional USD spent on making patients adherent (diabetes, hypertension, hyperlipidaemia).
in annual European cost from avoidable hospitalisations, emergency care and outpatient visits caused by non-adherence.
Medication is among the cheapest inputs in a chronic pathway and among the most consequential. When intake breaks down, the cost does not surface in the drug budget. It surfaces weeks later as an unplanned admission, an escalated therapy, or a diagnostic work-up that would not have been necessary. For an organisation that carries the cost risk for a population, those are exactly the lines that are not reimbursed away.
DoryGo makes intake visible as it happens. Missed and late doses appear within days rather than at the next refill, and your team decides whether and how to follow up — a phone call, a conversation with the pharmacy, a change of packaging. DoryGo records and displays; it does not interpret the data or recommend treatment. Whether better intake leads to fewer avoidable escalations in your population is an empirical question, and it is the question a pilot is designed to answer.
03 — The product
Three parts, one continuous record
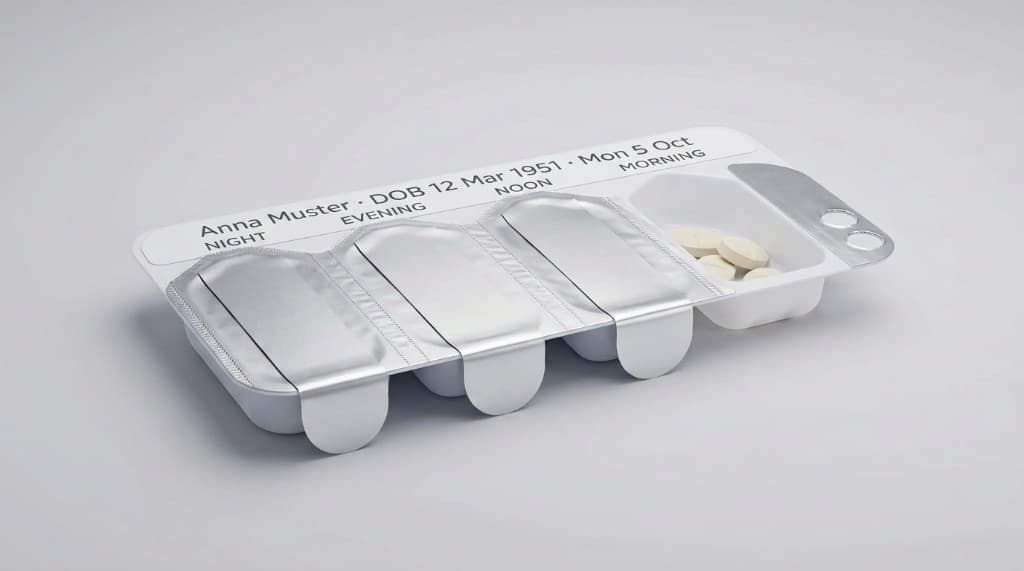
Pre-sorted multi-dose blister
A pharmacy sorts the full regimen into dated, time-labelled compartments, so the patient never assembles a dose themselves.
- —One compartment per intake time, printed with date and patient name
- —Regimen changes handled at the pharmacy, not by the patient
- —Removes the manual weekly re-sorting step entirely
Sensor pill box
A new blister is inserted each day. The box registers each compartment opening passively — no app step, no confirmation, nothing else for the patient to remember.
- —Timestamped event per opening, at compartment level
- —Local buffering; syncs when a connection is available
- —Works for patients who do not use a smartphone

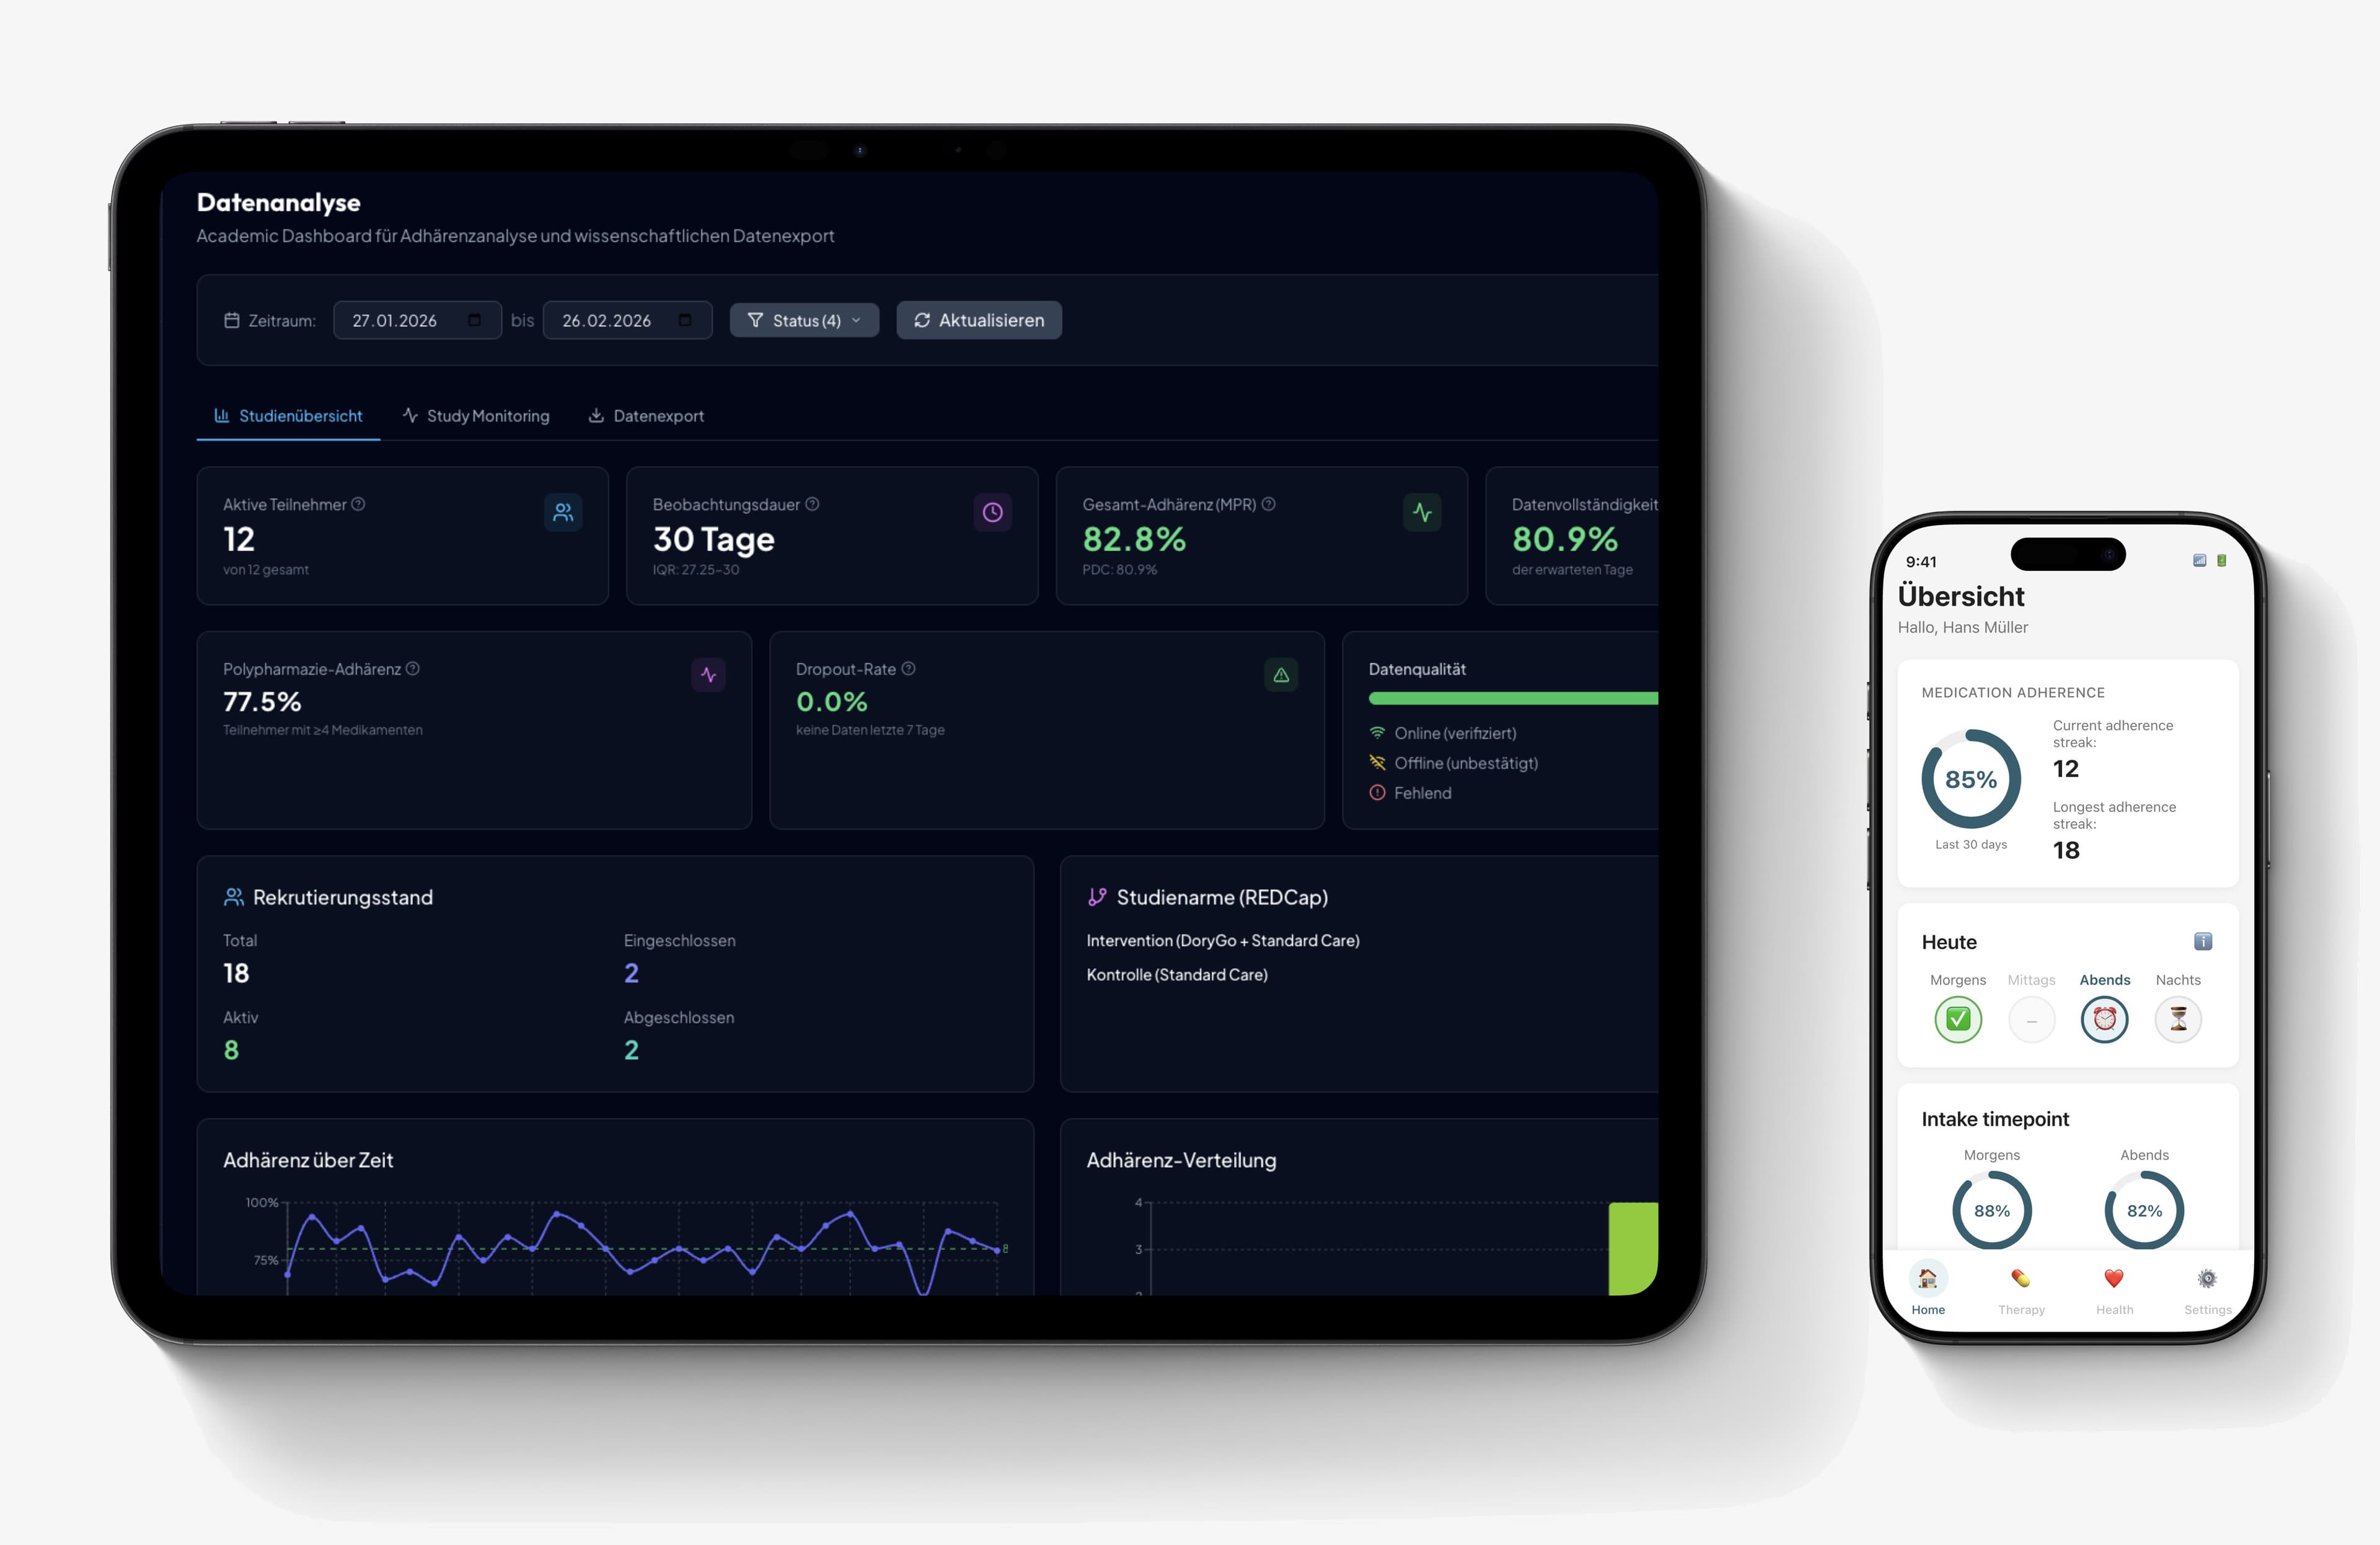
Patient app and dashboard
Patients see their own schedule and history. Your team sees recorded intake across all participating patients, sorted by missed and late doses.
- —Overview of all participating patients, sorted by missed and late doses
- —Intake history per patient
- —Role-based access; export via FHIR or CSV
04 — Workflow
From the pharmacy bench to your team, in five steps
05 — How step 1 is set up
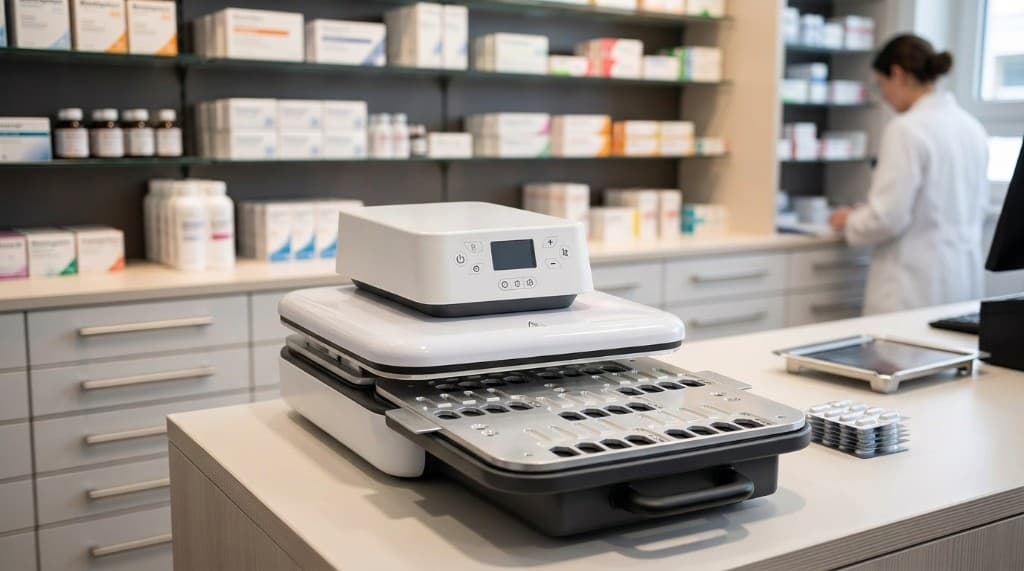
Blistering runs through a licensed pharmacy partner in your market
There is one route, and it is deliberate. The pre-sorting is carried out by a local, licensed pharmacy partner, which we identify and set up together with your organisation. Dispensing stays where it is already regulated and already trusted. We equip that pharmacy with the sealing machine, the blisters and the foils, and we supply the box, the app, the dashboard and the integration.
National rules for dispensing, repackaging and medical-device classification differ, and they determine what is possible in your market. We clarify this per country before a pilot is scoped, and say so plainly where something is not viable.
06 — Evidence
What is shown, and what is not
Both columns are part of the same answer, and they carry the same weight. We would rather you take the right-hand column into your evaluation than discover it later.
What we can show today
- The box records each compartment opening without any patient input, which removes self-report bias by construction.
- The full chain is built and working end to end: blister, sensor box, patient app, dashboard.
- In our own development testing, compartment openings were detected without error over several months of continuous bench testing, and battery life reached 18 months at four openings per day. These are internal measurements; independent validation is planned.
What we have not shown yet
- Any effect on treatment results. Whether a reliable record of intake improves them is the question our pilots are designed to answer.
- A validated cost-offset figure for a specific insured population. We will not quote an ROI we cannot defend.
- Long-run persistence: how intake behaves after two years of use.
- Deployment at the scale of a full health system.
07 — Pilot
What a first project looks like
- Cohort
- Patients on long-term medication, defined together with your clinical leads.
- Duration
- Pre-defined period of recording, plus a set-up and onboarding phase beforehand.
- What we measure
- Intake per dose and compartment, timing of each dose, data completeness, patient retention, and how quickly your team followed up on missed doses.
- What we provide
- Boxes, blister supply or partner coordination, patient onboarding material, dashboard access, and a named contact in Zurich.
- What we need from you
- A clinical owner, a data-protection contact, the cohort definition, and a team that follows up on missed doses during the pilot.
- What you get
- A dataset you own, a written read-out with the limitations stated, and a clear basis for deciding whether to scale or stop.
08 — Integration
Into the systems you already run
09 — Compliance
Where the data sits, and who may see it
10 — About us
Who you would be working with
DoryHealth is a small Swiss company based in Zurich. We build and operate DoryGo ourselves, which means a pilot is run by the people who built the product rather than handed to an implementation team.
11 — Contact
Request a scoping call
Thirty minutes, no slide deck. We ask about your cohort and your data environment, and tell you whether a pilot makes sense.
DoryHealth AG · Hagenholzstrasse 81a, 8050 Zürich
hello@doryhealth.com